

Rating: BEARISH | Target Price: $5.90 | Current Price: $15.52 | Implied Change: -62%
AUTHOR’S TAKE
The market is way too optimistic on Summit Therapeutics right now, pushing its valuation to an unsustainable $12 billion based entirely on a single drug called ivonescimab. Our short thesis is that investors are overlooking clear signs that this drug isn’t replicating its early clinical success as it transitions from small, isolated Chinese trials into large, global studies. The stock will face a reality check on November 14, 2026, the formal FDA PDUFA action date for ivonescimab paired with chemotherapy in first-line EGFR-mutated non-squamous non-small cell lung cancer. Because recent global data showed the drug failed to improve overall survival, we think a regulatory rejection or a highly restrictive label is the most likely outcome. If the remaining trials end up hitting similar roadblocks, the stock will likely lose all its premium and trade at a 10% to 15% discount to its cash value, putting our floor for the stock between $6.00 and $8.00 per share.
STRATEGY AND PIPELINE
Summit is a one-trick pony, and its survival depends entirely on ivonescimab and it’s 2 major phase 3 trials: HARMONi for non-squamous lung cancer and HARMONi-3 for frontline squamous lung cancer. Ivonescimab is a bispecific antibody engineered to hit both PD-1 and VEGF pathways. Instead of discovering its own treatments, the company changed its strategy a few years ago, dumped its old pipeline, and licensing this single molecule from a Chinese biotech called Akeso to get the rights in North America, South America, Europe, and Japan. The company’s business model relies on running late-stage Western clinical trials to clear regulatory hurdles and eventually generate revenue by launching the drug in these premium markets. However, because the company doesn’t have secondary platforms or fallback assets, it has no safety net if these multi-regional trials fail to duplicate the initial single-country data.
The drug’s MoA attempts to interrupt how tumors protect themselves and grow. Tumors routinely pump out a protein called vascular endothelial growth factor (VEGF) to sprout new blood vessels for their nutrient supply. This process changes the surrounding tissue into an environment that blocks immune cells from working properly. At the same time, tumors use a checkpoint protein called programmed death-ligand 1 to bind with PD-1 receptors on T cells, which switches off the body’s natural immune response. Ivonescimab is built as a single antibody that attaches to both targets at once. When the drug locks onto VEGF, it changes shape slightly, which makes it bind even tighter to PD-1.
CLINICAL PERFORMANCE AND METHODOLOGY
In the phase 3 HARMONi study, the trial was designed with dual primary endpoints of progression-free survival (PFS) and overall survival (OS). While PFS acts as a surrogate endpoint that is faster to measure, the FDA views OS as the ultimate gold-standard clinical outcome, which means this is good endpoint selection.
The drug hit its surrogate mark, reducing the risk of disease progression by 48% with a PFS hazard ratio of 0.52. At the World Conference on Lung Cancer, the final analysis for the global phase 3 HARMONi trial showed that adding ivonescimab to chemotherapy failed to reach a statistically significant overall survival benefit, registering an unapproved p-value of 0.0570 and a hazard ratio of 0.79 with a wide 95% confidence interval stretching from 0.62 to 1.01. This is very problematic since the FDA regularly blocks full approval or severely restricts market access for cancer drugs that offer a temporary progression-free survival extension but fail to prove that patients actually live longer.
Furthermore, during its Q1 2026 earnings cycle, Summit disclosed that the interim progression-free survival analysis for the squamous group in HARMONi-3 missed the statistical threshold required to stop the trial early for efficacy. The study now has to run to its full readout, showing that the real-world treatment effect is far more variable in Western patients than early data suggested. To make the representation matters worse, the supportive datasets generated by Akeso enrolled 100% Asian patients, and this lack of demographic diversity makes the data unrepresentative of Western patient populations, where genetic diversity, baseline smoking habits, body weights, and tumor mutational landscapes are very different.
Even worse, subgroup data from the related HARMONi-6 trial showed a strong 60% progression-free survival benefit for patients under 65, but that benefit dropped to just 12% for patients aged 65 and older. Because lung cancer mostly impacts elderly patients, this drop-off damages the actual addressable market.
Yet another blow is the safety data published in The Lancet showed that 69.2% of patients in the ivonescimab arm experienced grade 3 or higher treatment-related adverse events. More importantly, treatment-related serious adverse events (TRSAEs) spiked to 20.8% in the bispecific cohorts. The anti-VEGF component introduces structural vascular complications, causing severe grade 3/4 hypertension in 5% of patients and life-threatening active hemorrhages or pulmonary bleeding in 24.8% of the trial population, and it’s well known that combining anti-VEGF and anti-PD-1 mechanisms triggers predictable toxicities like grade 3/4 high blood pressure, severe protein in the urine, internal tissue tears, and dangerous lung bleeding, which will limit adoption in community clinics.
MOAT, IP, REGULATION, AND STRUCTURAL ADVANTAGES
Summit’s competitive position relies on territory licensing deals rather than a unique technology platform. Large pharmaceutical competitors don’t need to copy ivonescimab directly since companies like AbbVie are already advancing their own next-generation PD-1/VEGF bispecifics.
Regulatory trends are also turning into a headwind. Under strict Project Pragmatica guidelines, the FDA places much less weight on localized, single-country datasets when global trials reveal geographic differences or lack a clear survival benefit. Summit also faces operational risks because it relies on third-party facilities and remains dependent on Akeso’s supply chain in China for primary production. Any technical scaling issues or failed pre-approval inspections at these sites could disrupt commercial timelines, leaving Summit with few structural options to sustain its current valuation.
THE BULL CASE
The bull case assumes that the FDA ignores the lack of mature overall survival data in the global HARMONi trial and grants a broad label on November 14, 2026. For the stock to re-rate toward a range of $31.00 to $38.00, the final readout of HARMONi-3 in late 2026 would need to deliver an unexpected survival benefit that reverses the interim trends. This outcome would require the market to view the lower efficacy in patients over 65 as a statistical anomaly and assume that community oncologists will comfortably manage the drug’s high-grade toxicity profile, both of which seem very unlikely to happen.
THE BEAR CASE
The bear case is driven by the single-asset concentration risk and recent clinical shortfalls. The primary risk is a CRL from the FDA this November due to the lack of overall survival evidence in the global registration trial, which would likely lead to a steep devaluation of the stock. As final data from HARMONi-3 comes in, it may confirm that the drug faces difficulties outperforming standard pembrolizumab regimens in a Western demographic. With an accelerating cash burn and no incoming product revenue, a clinical failure would likely cause the stock to trade at a 10% to 15% discount to its cash value, bringing the share price down to a floor of $6.00 to $8.00.
A similar historical precedent for this would be BeyondSpring, a biotech company whose valuation surged in 2021 based on spectacular clinical data for its lead asset, plinabulin, which was generated almost entirely within single-country trial sites in China. Much like Summit, the market focused on the localized efficacy and ignored the geographic concentration. When the company submitted its package, the FDA handed them a stark CRL, declaring that data from homogeneous Chinese cohorts did not prove safety and efficacy for Western demographics and mandating a new global trial. The stock plunged 56% in a single day, bleeding out continuously over the following months to trade at a severe discount to its cash balance as the pipeline premise dissolved. If ivonescimab faces a regulatory rejection based on geographic and demographic data requirements, Summit’ll likely get the same re-rating.
FINANCIAL POSITION, UNIT ECONOMICS, AND RUNWAY
Summit ended its recent operating period with approximately $545.9 million in cash and short-term liquid equivalents against $101.9 million in total liabilities. However, their annual burn rate of $323.5 million limits their true cash runway to roughly 1.6 years, a dangerously tight window given the timeline required to establish a commercial launch infrastructure.
Another bad sign was in June 2026 when management abruptly withdrew a proposed $500 million underwritten public stock offering just 24 hours after its announcement, citing unfavorable market conditions. Along with the burn rate, this sudden withdrawal indicates a near-term capital shortfall that must be addressed, and as Summit has no active product revenue to offset its operational burn, the company’ll be forced to dilute shareholders through potential secondary offerings or private placements executed at a steep discount if regulatory milestones slip.
MARKET AND COMPETITION
The frontline non-small cell lung cancer market is an absolute dogfight dominated by massive pharmaceutical players. To even try to sway oncologists, Summit needs an undeniable efficacy or safety profile, but the numbers are moving in the wrong direction. Community oncologists are notoriously risk-averse and won’t throw out Merck’s established frontline Keytruda regimen—which has a rock-solid, ten-year survival database and a severe adverse event rate routinely under 10%—for a highly toxic bispecific that has failed to show a definitive survival benefit in global testing. Ivonescimab completely missed on overall survival in the global HARMONi trial, posting a non-significant hazard ratio of 0.79 (p=0.0570), and cancer drugs simply cannot displace entrenched market leaders if they fail to prove patients live longer. Meanwhile, its safety profile is a total disaster compared to standard PD-1 monotherapies, carrying a brutal 69.2% rate of grade 3 or higher severe adverse events where 24.8% of patients experience active hemorrhages and internal bleeding due to the anti-VEGF overlap. This same commercial reality blunts Summit’s ability to compete with alternative niches like Johnson & Johnson’s Rybrevant, which owns solid, non-chemotherapy baseline survival data in specific EGFR sub-mutations without introducing massive systemic bleeding risks.

KEY CATALYSTS AND TIMELINE
H2 2026: Final progression-free survival data readout from the squamous cohort of the global phase 3 HARMONi-3 trial.
H2 2026: Interim overall survival data readout from the multi-regional HARMONi-3 trial.
November 14, 2026: FDA PDUFA binary action date for ivonescimab plus chemotherapy in EGFR-mutated non-squamous NSCLC.
Early 2027: Initial top-line clinical readouts from the phase 2 trials evaluating ivonescimab in metastatic colorectal cancer.
VALUATION
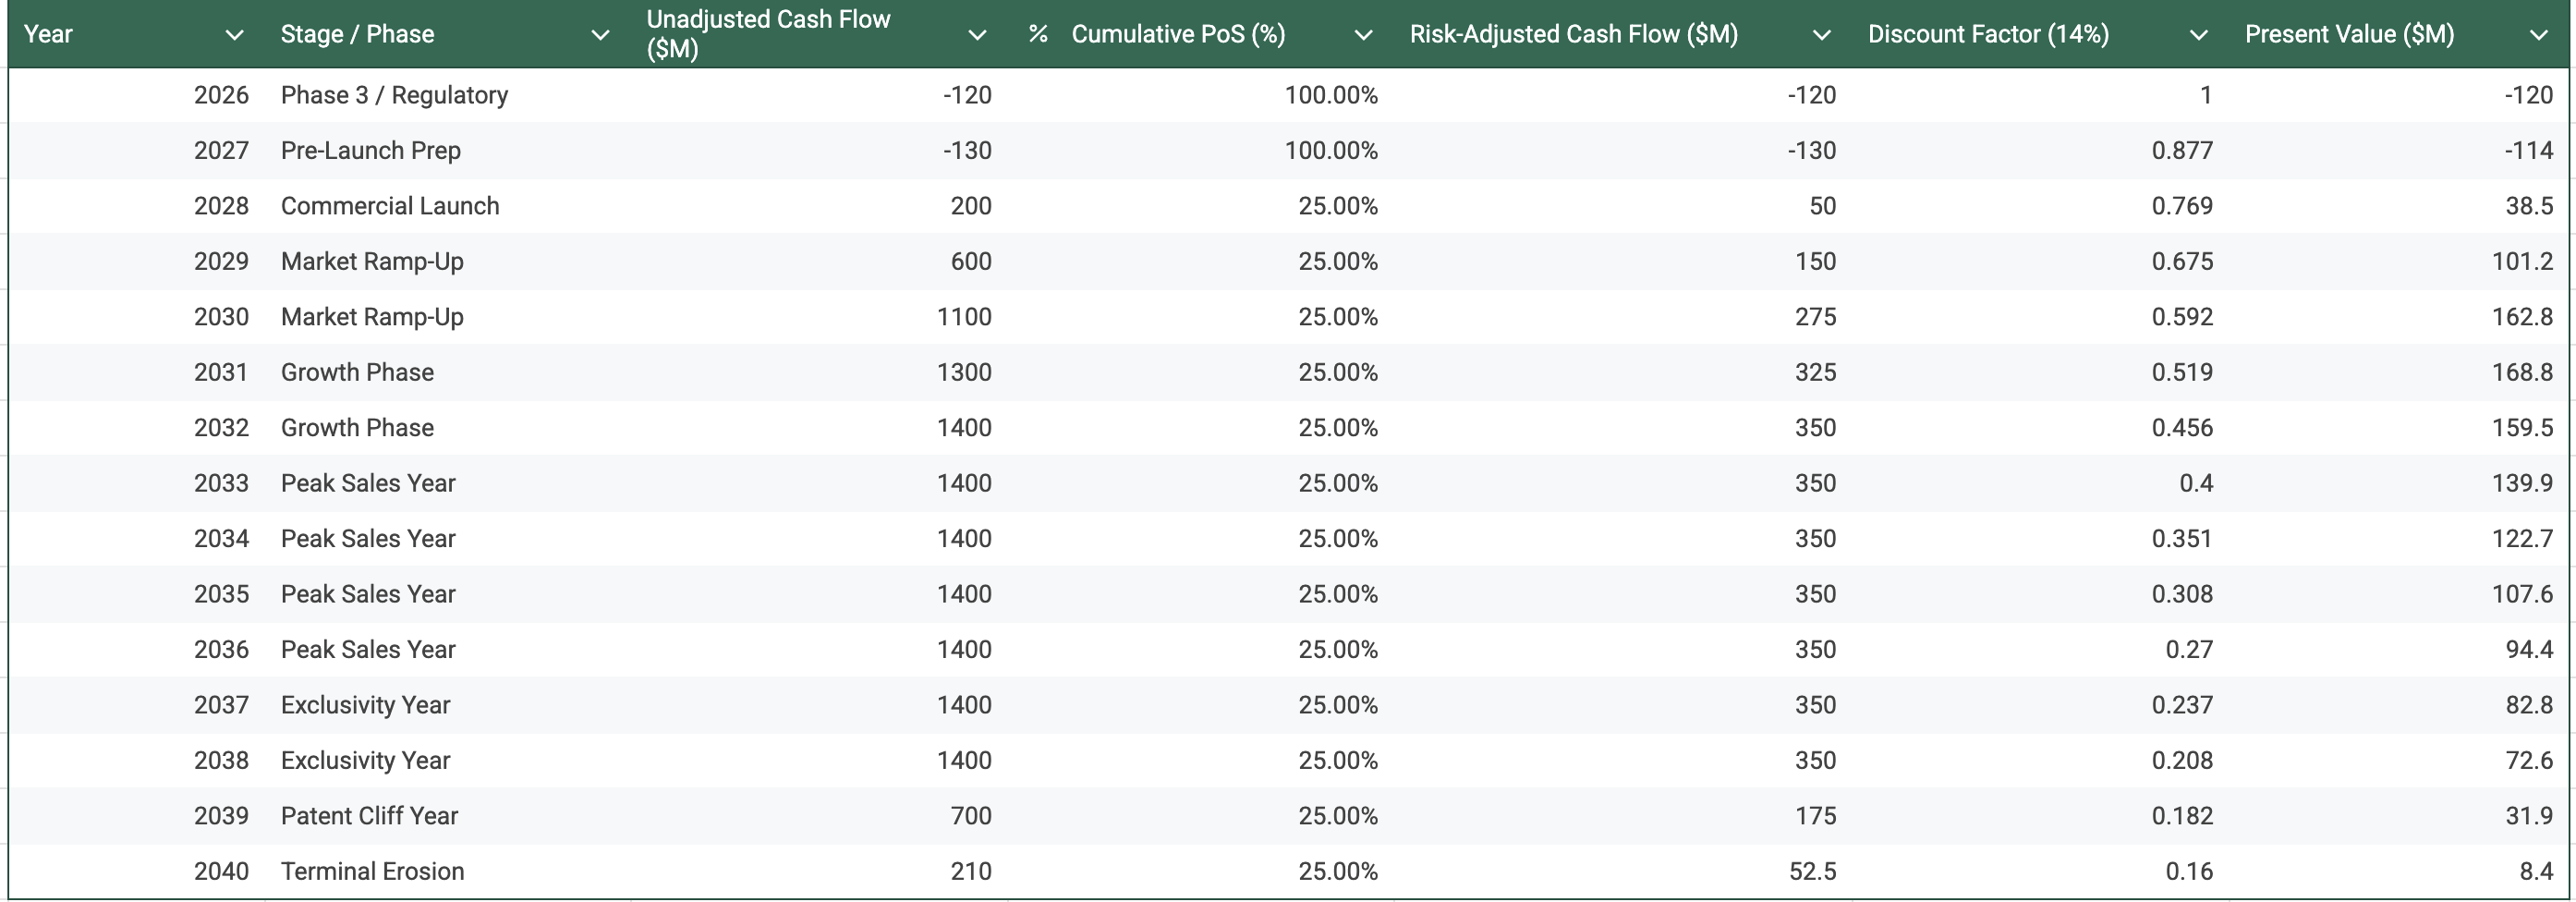
The timeline table below tracks the projected cash flows, cumulative probabilities of success, risk-adjusted values, and discounted present values for the asset through the end of its lifecycle in the terminal year.
Sensitivity Analysis
Assumptions Summary Table
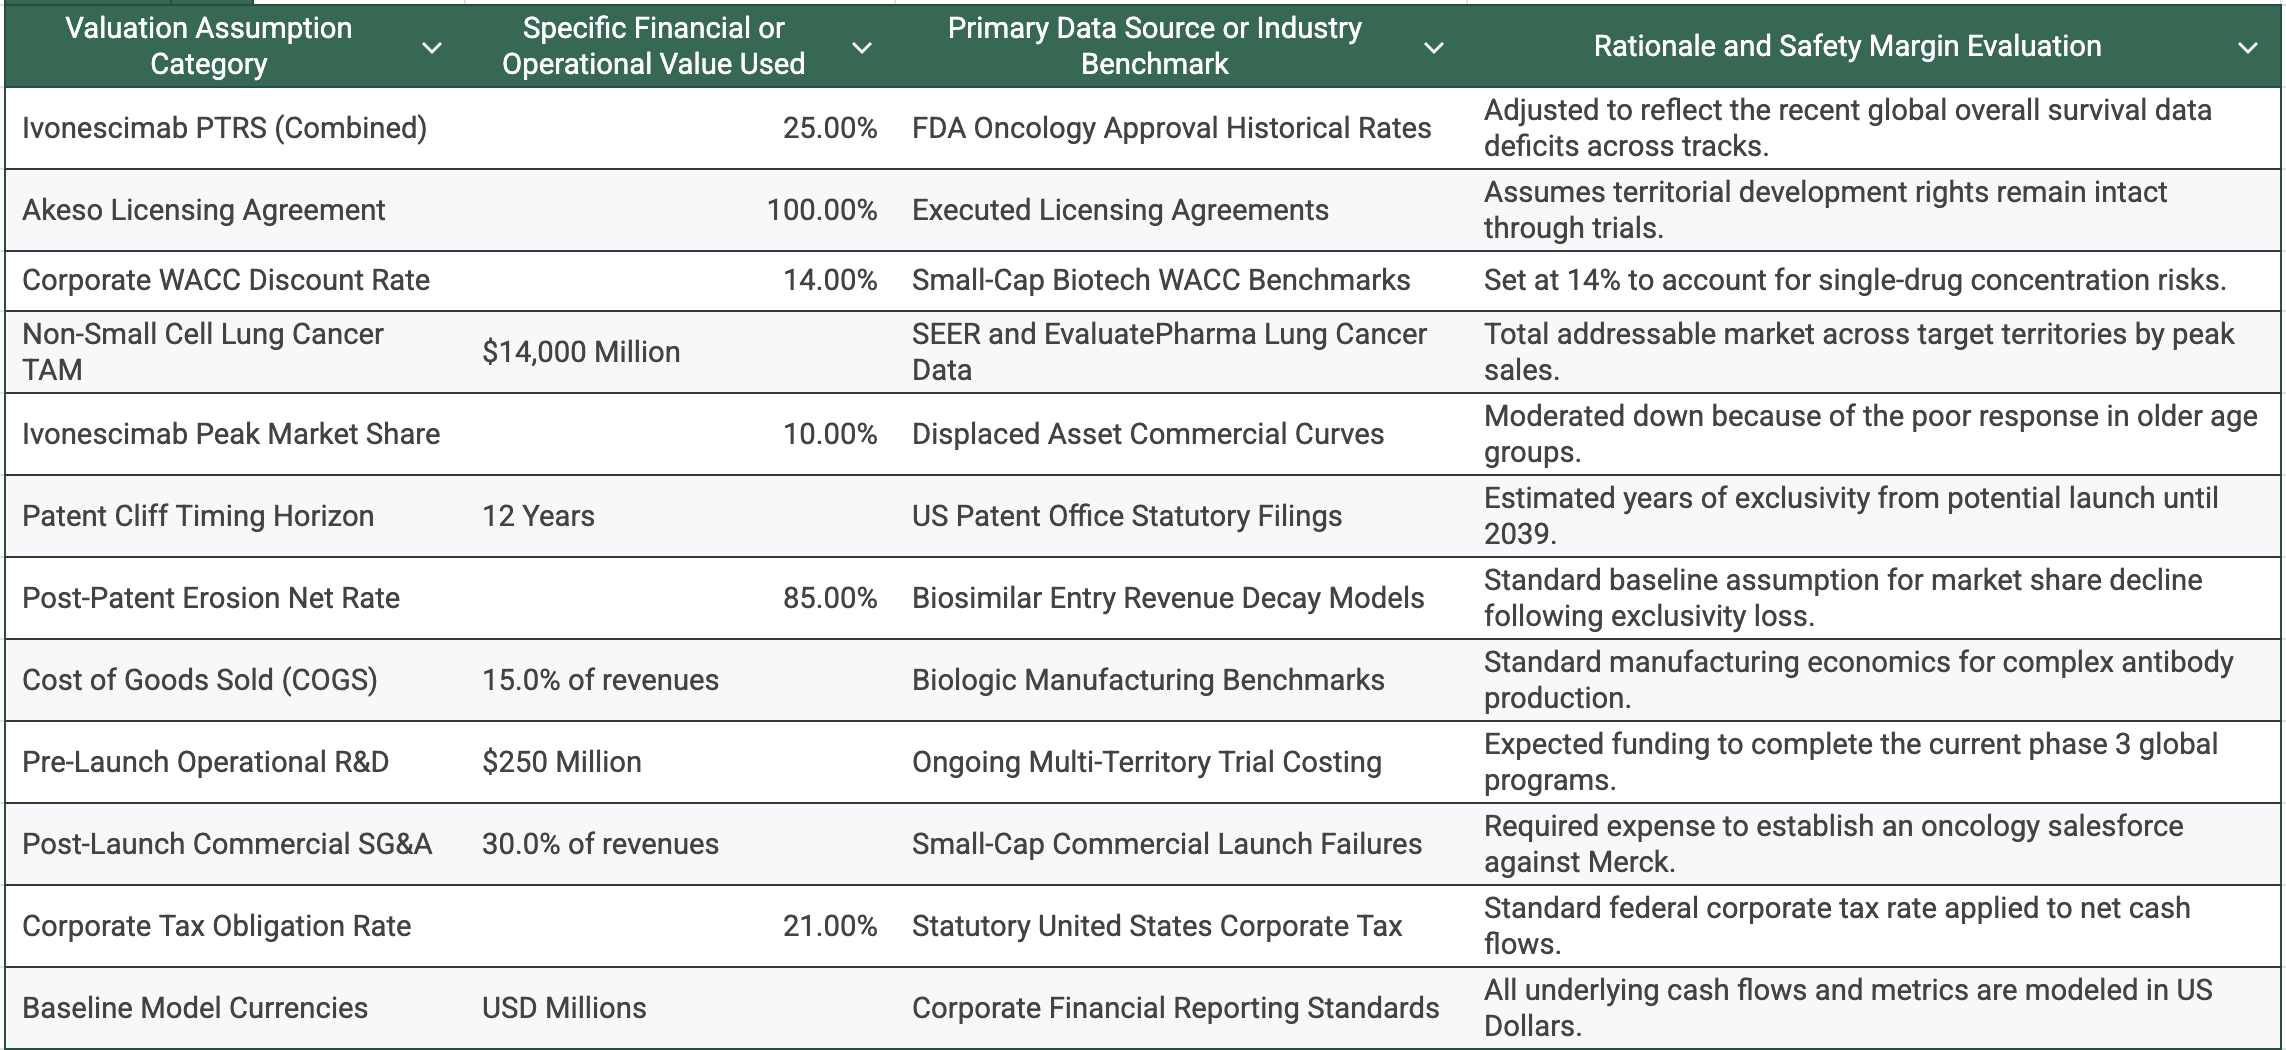
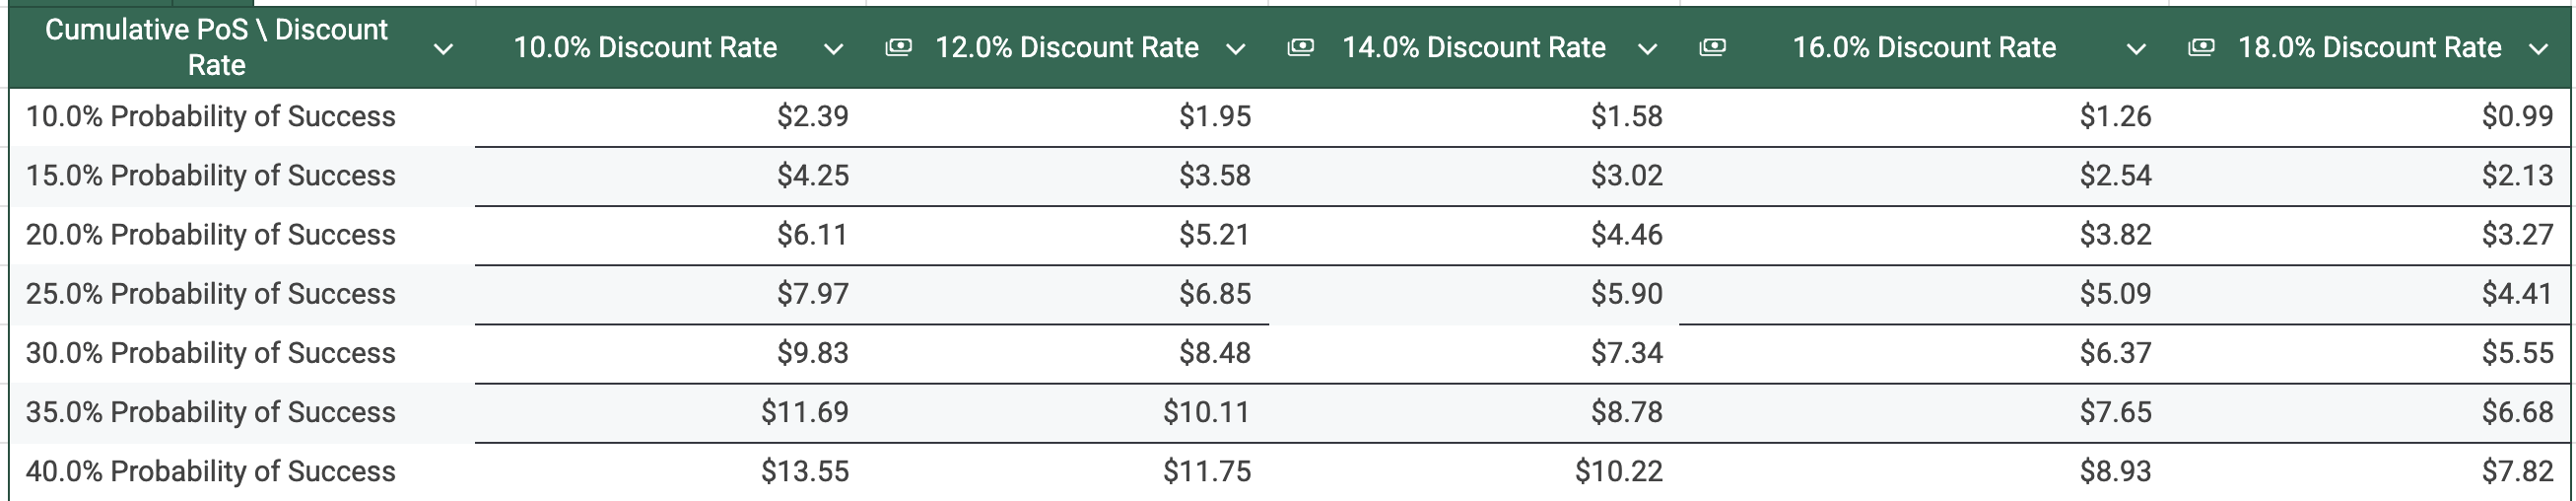
The final target price of $5.90 is based on a 14% discount rate and a 25.0% combined PoS.
Disclosure
This Due Diligence report is for informational purposes only and does not constitute financial advice or a recommendation to buy, sell, or hold any securities. The information is based on public filings and media reports and may not be exhaustive or entirely accurate. Investing in biotechnology companies, especially those in clinical stages of development, involves inherent risks, including the complete loss of capital. Clinical trial outcomes, regulatory pathways, and eventual commercial success are subject to uncertainty. Readers should conduct their own thorough due diligence and consult with a qualified financial advisor before making any investment decisions. The author may hold long or short positions in Summit Therapeutics ($SMMT) and has received no compensation for this report.
The BeyondSpring parallel is a sharp catch, and honestly this is a level of clinical rigor most retail biotech coverage doesn’t come close to. Outside my lane to have a real view on the trial data itself, but great article!
agree 100%