

Rating: BULLISH | Target Price: $6.35 | Current Price: $2.13 | Implied Upside: +198%
AUTHOR’S TAKE
In short, yes. We are staying highly bullish on Compass Therapeutics with an updated $6.35 target price, which means we see a massive 198% upside from the current trading price of $2.13. The market panicked after the late April 2026 secondary survival endpoint miss for tovecimig in the COMPANION-002 trial for second-line biliary tract cancer, punishing the stock with a brutal 65% sell-off, and the stock has been relatively stable since then. While the raw intent-to-treat overall survival hazard ratio of 1.05 looked bad on the surface, investors are ignoring an unprecedented 56% reduction in the risk of disease progression, a spectacular progression-free survival benefit, and a massive 54% control-arm crossover that mathematically corrupted the survival data. The big near-term catalyst to watch is the upcoming pre-Biologics License Application meeting with the FDA in late 2026. If the agency accepts a filing based on the clean progression-free survival and objective response rate data, it will likely trigger a rapid re-rating. Downside risk is beautifully protected here by a hard valuation floor of $195 million in cash and marketable securities as of March 31, 2026, which values the equity right near its liquid cash line and gives us an incredibly asymmetric risk-reward setup.
STRATEGY AND PIPELINE
Compass Therapeutics is a clinical-stage biotech company that focuses on finding and developing proprietary antibody therapies to treat various human cancers. The team uses an internal antibody discovery engine to build bispecific and monoclonal antibodies that jumpstart the immune system, stop tumors from growing new blood vessels, and knock down the defenses cancers use to hide from the immune system. Compass makes money by moving these proprietary oncology candidates through clinical development toward regulatory approval and eventual commercial launch, though they also look for opportunities to lock in out-licensing deals, milestone payments, and royalties through global pharmaceutical partnerships. Strategically, the company has successfully evolved from an early-stage discovery platform into a late-stage development engine that focuses heavily on bispecific designs capable of hitting two angiogenic and checkpoint networks at the exact same time. The flagship of this pipeline is tovecimig, an investigational bispecific antibody designed to block Delta-like ligand 4 and Vascular Endothelial Growth Factor A simultaneously. This dual action blocks tumor blood supply while reversing the immunosuppression that standard tumors use to thrive. Behind this lead asset, Compass is expanding its reach through CTX-8371, a bispecific targeting both PD-1 and PD-L1 to choke off the checkpoint pathway from both sides, and CTX-10726, a tetravalent bispecific that combines PD-1 and VEGF-A targeting to disrupt tumor blood flow while supercharging tumor-infiltrating lymphocytes. Each of these assets is critical because they offer specific, unified mechanisms designed to beat standard-of-care chemotherapies in highly vascular, drug-resistant solid tumors.
CLINICAL PERFORMANCE AND METHODOLOGY
The bedrock of the clinical thesis is the Phase 2/3 COMPANION-002 randomized, controlled trial, which evaluated 168 patients with advanced, unresectable, or metastatic biliary tract cancer who had already failed one prior systemic therapy line. Patients were randomized 2:1 to receive either tovecimig alongside paclitaxel or paclitaxel alone as a monotherapy control, with a clear protocol provision allowing control patients to cross over to the active tovecimig arm the moment central imaging confirmed their disease was progressing. Topline results showed the trial cleanly met its primary endpoint of objective response rate, delivering a 17.1% response rate in the tovecimig combination group versus a tiny 5.3% in the paclitaxel control group, proving a statistically significant benefit with a p-value of 0.031. Looking at the secondary endpoints, the data cutoff showed an incredibly strong, statistically significant improvement in progression-free survival via blinded central review, with a median progression-free survival of 4.7 months for the tovecimig combination compared to 2.6 months for the control arm, yielding a stunning hazard ratio of 0.44 and a p-value under 0.0001.
However, the trial missed its secondary endpoint of overall survival, with a median overall survival of 8.9 months in the tovecimig group compared to 9.4 months in the control group, leading to an intent-to-treat hazard ratio of 1.05 and a p-value of 0.78. The regulatory reality is that these raw survival numbers were heavily contaminated because 31 out of the 57 control patients crossed over to take active tovecimig after progressing, which means 85% of all patients in the entire study were exposed to the drug. A post hoc subset analysis of the control group revealed that patients who crossed over achieved a median overall survival of 12.8 months compared to just 6.1 months for those who never took tovecimig, creating a clear hazard ratio of 0.54 and a p-value of 0.04. Furthermore, a deep dive into post-crossover performance showed that patients achieved a median progression-free survival of 3.5 months after crossing over, compared to a meager 1.9 months on their initial paclitaxel monotherapy, locking in an impressive hazard ratio of 0.36 and a p-value of 0.0016.
While short-biased critics point to post hoc statistical corrections like the Rank-Preserving Structural Failure Time model as being uninterpretable, the underlying biological signal is undeniable. On the safety front, the combo showed a predictable, manageable profile, though dual DLL4 and VEGF-A inhibition does bring class-related side effects. Total hypertension rates reached 69% across all grades, with a grade 3 or higher rate of 44%, while severe neutropenia clocked in at 36% for grade 3 or above. These rates are high, but they match what clinicians expect when combining anti-angiogenics with chemotherapy. What remains up in the air is whether the FDA will accept this highly confounded survival data at the upcoming meeting or demand a brand-new randomized trial without crossover before accepting a Biologics License Application.
MOAT, IP, REGULATION, AND STRUCTURAL ADVANTAGES
Compass protects its business with a mix of proprietary antibody engineering platforms, strict intellectual property barriers, and specialized regulatory advantages. The company owns a massive web of granted patents and active patent applications worldwide that safeguard the composition of matter, genetic sequences, and direct use methods for tovecimig, CTX-8371, and CTX-10726. Tovecimig’s core composition patents run deep into the 2030s, meaning competitors cannot easily copy the precise binding speeds and affinity levels created by Compass’s discovery engine. This platform fine-tunes dual-targeting systems to avoid the dangerous systemic safety issues that pop up when doctors try to blend separate anti-angiogenic and immunotherapy drugs manually. On top of patent law, tovecimig holds powerful structural regulatory shields, including a Fast Track Designation granted in April 2024 and an Orphan Drug Designation handed out in April 2026 for advanced biliary tract cancer. Orphan status locks in seven full years of market exclusivity in the United States post-approval, waves expensive regulatory user fees, and provides generous tax credits for clinical trials. These benefits create enormous cost and time walls that keep biosimilar developers from easily touching the company’s target market.
THE BULL CASE
The bull case is incredibly straightforward and rests entirely on the FDA looking at the COMPANION-002 data, recognizing that the overall survival numbers were completely masked by the 54% crossover rate, and agreeing to focus on the spectacular, unconfounded progression-free survival hazard ratio of 0.44 and the tripled objective response rate. In this scenario, the late 2026 pre-Biologics License Application meeting ends with a green light from the FDA to submit the marketing package based on the data in hand, leading to an official filing acceptance in early 2027. This regulatory victory would spark an explosive institutional re-rating, forcing Wall Street to price in a real commercial launch for second-line biliary tract cancer by late 2027 or early 2028. Since there are zero effective, targeted second-line options for all-comer patients, tovecimig would rapidly dominate this high-value market. At the same time, Phase 1 updates from the CTX-8371 and CTX-10726 programs will show real clinical validation, proving the company has a true multi-asset platform. Backed by near-term commercial visibility and early pipeline wins, the market will re-rate the stock up to a high-side valuation range of $6.50 to $8.00 per share, completely erasing the recent panic selling.
THE BEAR CASE
The bear case plays out if the FDA takes an inflexible, strictly traditional stance during the late 2026 pre-Biologics License Application meeting. The agency could reject the filing entirely, arguing that under Project Optimus guidelines, a numerical disadvantage in intent-to-treat overall survival cannot be ignored and that post hoc crossover adjustments are simply not enough to save a trial that missed a key survival endpoint. The FDA would then issue a firm mandate requiring Compass to run an entirely new, fully powered Phase 3 trial from scratch, this time completely banning any patient crossover to prove a clean survival benefit.
A regulatory setback like this would destroy the commercial timeline for tovecimig, pushing a potential launch back by at least four to five years. Facing an incredibly long and expensive clinical path, management would have no choice but to shelve or delay the tovecimig program to save cash, forcing an immediate pivot to early-phase assets like CTX-8371 and CTX-10726. This forced shift would trigger heavy analyst downgrades and a wave of institutional selling, dragging the stock down to a distressed bear-case range of $1.00 to $1.20 per share, where it would trade well below its liquid cash value as a broken clinical story.
FINANCIAL POSITION, UNIT ECONOMICS, AND RUNWAY
Compass boasts a solid balance sheet that serves as a safety net, finishing the first quarter of 2026 on March 31 with $195 million in cash and marketable securities and absolutely zero debt. For the quarter, the company posted a net loss of $18.3 million, or $0.10 per share, compared to a net loss of $16.6 million in the first quarter of 2025. Clinical R&D spending remained highly controlled, climbing just 3% to $13.4 million, while general and administrative costs jumped 41% to $6.9 million. This G&A spike was driven by $1.0 million in early pre-commercialization infrastructural spending and higher stock-based compensation. Operating cash burn is trending right around $18 million per quarter, making management’s guidance of a cash runway stretching out into the first half of 2028 mathematically airtight. While short sellers point out the risk of squandering this cash on early pre-commercialization infrastructure for a potentially unlaunchable product, this cash buffer gives the company power because it removes any near-term dilution or financing pressure, giving management the time and flexibility to navigate the FDA or comfortably pivot operations without needing to raise dilutive capital at a low stock price.
MARKET AND COMPETITION
The global market for biliary tract cancer is a massive area of unmet clinical need, characterized by incredibly low survival rates and few real treatment options. Frontline therapy (1L) has standardized around a combination of durvalumab (Imfinzi) plus gemcitabine/cisplatin (GemCis). This means almost all patients progressing into the 2L setting are immune-checkpoint inhibitor (ICI) experienced.
While this alters the biological profile of the tumor microenvironment, tovecimig’s anti-angiogenic mechanism (DLL4 x VEGF-A) acts independently of prior checkpoint exposure, providing a robust rationale for all-comer clinical activity. To expand on this option, Compass is actively pursuing frontline validation via an investigator-sponsored trial (IST) combining tovecimig directly with the 1L Durvalumab + GemCis standard, positioning the drug to potentially shift from a 2L rescue option to a multi-line blockbuster.
The competitive landscape highlights how well tovecimig stacks up against the current alternatives:
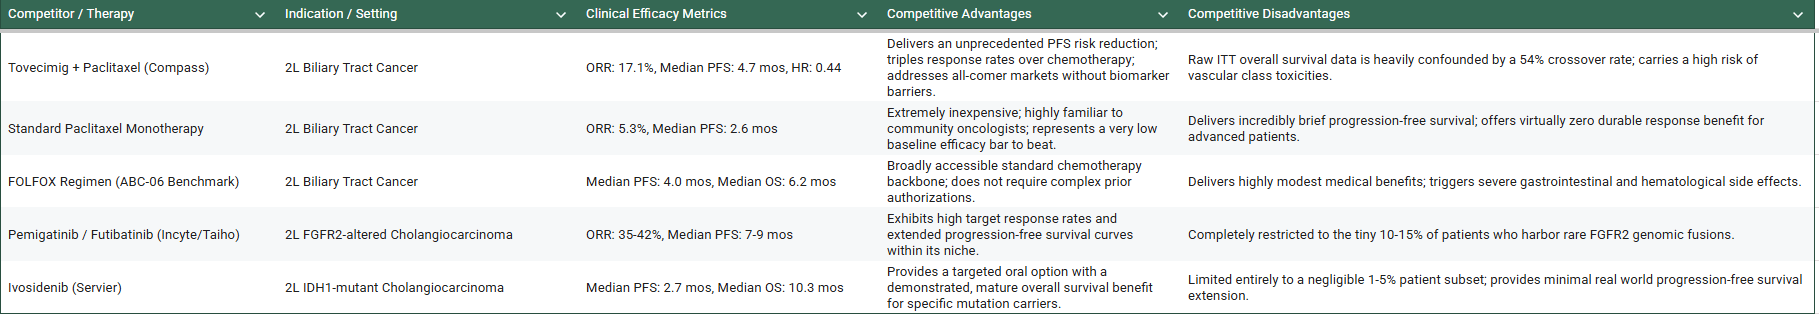
Compass has a clear path to win because tovecimig is designed as an all-comer therapy that does not require specialized biomarker genetic testing, giving it direct access to the 85% of second-line patients who lack actionable mutations. The company could lose if the uninterpretable raw overall survival data leads to total regulatory rejection or if high rates of severe vascular toxicities push doctors to stick with safer, albeit less effective, generic therapies.
KEY CATALYSTS AND TIMELINE
Q2 2026: Full presentation of the CTX-8371 Phase 1 dose-escalation and cohort expansion data in advanced solid tumors at the ASCO Annual Meeting.
Mid-2026: Launch of the Phase 2 clinical basket trial testing tovecimig across a broader set of DLL4-positive solid tumor indications.
Mid-2026: Initiation of the Phase 2 clinical trial evaluating the CD137 agonist CTX-471 in solid tumors expressing neural cell adhesion molecule CD56.
Late 2026: Pivotal pre-BLA meeting with the FDA to finalize the regulatory path and viability of the tovecimig data package.
Q4 2026: Initial clinical readouts and safety data from the CTX-10726 Phase 1 multiple ascending dose study in post-checkpoint inhibitor settings.
Early 2027: Expected formal submission of the tovecimig Biologics License Application following a successful regulatory meeting.
SUM-OF-THE-PARTS RISK-ADJUSTED NET PRESENT VALUE (rNPV) ANALYSIS
Tovecimig Assumption Profile and Operational Logic
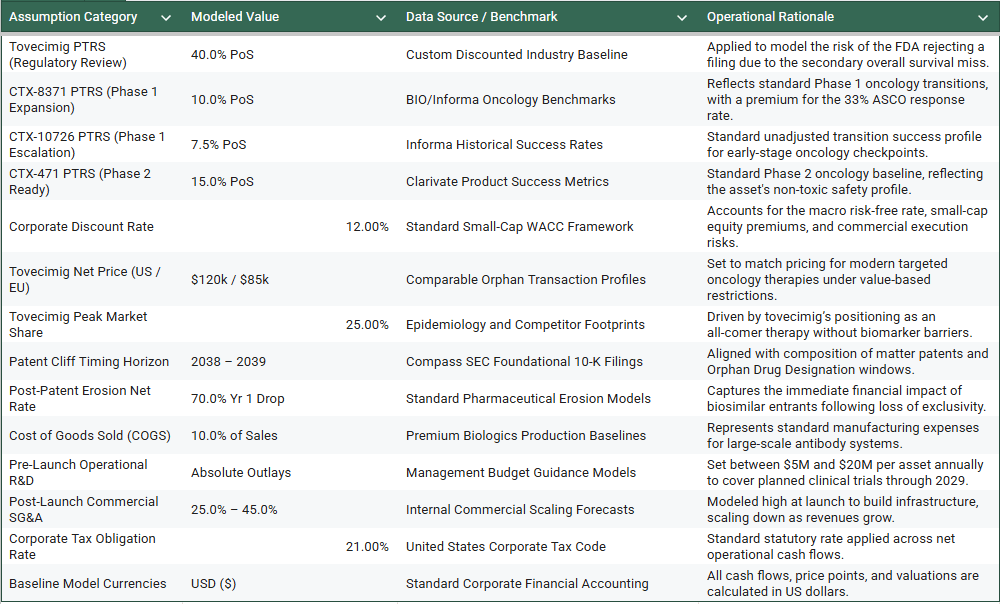
When we look at the numbers for tovecimig, the whole valuation model comes down to how we treat the data from the Phase 2/3 COMPANION-002 study alongside standard industry templates. Since the trial has already run its course, we don’t need to worry about early-stage attrition; those milestones are already in the rearview mirror. Instead, our Probability of Technical and Regulatory Success is entirely focused on the upcoming regulatory review phase. Normally, an oncology drug that hits its primary endpoint with a massive progression-free survival benefit enjoys an 85% to 90% chance of approval. But because a 54% control-arm crossover heavily muddied the water on overall survival, we are tossing out the optimistic standard. We are using a conservative 40% regulatory Probability of Success to reflect the risk of the FDA pushing back under Project Optimus guidelines during the late 2026 pre-BLA meeting. If they get through that gate, the launch probability is 100%, keeping the cumulative probability of success for the rest of the asset’s life at a flat 40%. In our internal sensitivity modeling, we let this baseline swing between a pessimistic 25% if the FDA demands a brand-new trial, up to a more optimistic 60% if regulators choose to focus heavily on that clean 0.44 progression-free survival hazard ratio.
On the commercial side, we are defining the target footprint purely as second-line advanced or metastatic biliary tract cancer. To map out the market size, we started with an annual incidence of roughly 12,000 patients in the United States and 15,000 across Europe. Looking at historical registries, about 60% of these individuals will progress past frontline standard-of-care therapies—which have now shifted to durvalumab plus gemcitabine/cisplatin—and still be healthy enough to seek second-line rescue options, giving us a baseline addressable universe of roughly 16,200 eligible patients every year. We expect tovecimig to capture a 25% peak market share. This number was chosen because, unlike niche competitors like pemigatinib or ivosidenib that are strictly limited to tiny 10% or 5% biomarker sub-populations, tovecimig works as an all-comer therapy regardless of prior immunotherapy exposure.
For unit pricing, we are assuming a net annual treatment course cost of $120,000 in the United States and a lower cross-border European price of $85,000, which reflects the stricter, value-based reimbursement realities across the EU. This drives our global peak sales estimate to $385.0 million in unadjusted dollars. We expect the drug to reach this peak 5 years after its projected 2028 launch, hitting maximum saturation in 2033. The launch trajectory follows a standard log-linear curve where the asset captures 15% of peak sales in Year 1, 35% in Year 2, 55% in Year 3, 80% in Year 4, and hits full capacity in Year 5. This easily fulfills the industry benchmark of crossing the 50% peak sales threshold between its second and third year on shelves.
The overall timeline is bounded by a robust intellectual property moat, including foundational composition of matter patents running through the mid-2030s and a 7-year post-approval US Orphan Drug Designation window. This pushes our projected patent cliff timing out to the year 2038. Once that cliff hits, the model assumes immediate biosimilar entry, driving a steep post-patent erosion rate where revenues plunge 70% in the first year and another 20% in the second, effectively zeroing out the asset’s terminal value by 2040. We are assigning a 100% scenario weight to this base case to keep the model grounded strictly in the trial’s core metrics.
To discount these future cash flows back to 2026 dollars, we are using a 12% discount rate. This percentage factors in the current macro risk-free rate, a small-cap biotech equity risk premium, and an extra buffer for execution risk since Compass does not yet have an established in-house sales team. For unit economics, we are modeling a Cost of Goods Sold at 10% of revenue, which is standard for premium large-scale biologics manufacturing. Before the launch, we are locking in future R&D cash outlays at absolute values of $20.0 million annually through 2027 to cover regulatory filing prep and the final closeout of the trial infrastructure. Post-launch, we assume commercial SG&A will consume 45% of incoming sales during the initial 2028 rollout to pay for team expansion, before tapering down to a mature long-term run rate of 25% as the commercial engine scales up. All net operating profits are hit with a standard 21% US corporate tax rate, and all currency assumptions are settled exclusively in USD.
CTX-8371 Assumption Profile and Operational Logic
The financial engine for CTX-8371, the company’s bispecific antibody hitting both PD-1 and PD-L1, is built directly around the highly encouraging clinical signals showcased at the ASCO 2026 Annual Meeting. Right now, the asset is moving through Phase 1 expansion cohorts, capturing 28 triple-negative breast cancer patients, 28 non-small cell lung cancer patients, and 12 Hodgkin Lymphoma patients. Because it is still early in the clinical lifecycle, we have to look closely at phase-by-phase attrition and termination risks. Using historical BIO/Informa benchmarks for early oncology therapeutics, we have modeled a 65% success rate for the Phase 1-to-Phase 2 transition, 30% for Phase 2-to-Phase 3, 50% for Phase 3 completion, and 85% for final regulatory review. Compounding these individual steps yields a raw mathematical probability of success of 8.29% from Phase 1 to approval. However, because the dose-escalation phase showed a striking 33% objective response rate at the highest cohorts, we rounded this up to a premium baseline of 10% Probability of Success. In our internal sensitivity checks, we stress-test this parameter by sweeping it between a conservative 5% floor and a best-in-class 15% ceiling.
Our commercial strategy targets a market defined as advanced solid tumors that have become completely refractory to standard immune-checkpoint inhibitors. Across the specific target niches of TNBC, NSCLC, and Hodgkin Lymphoma, the combined annual post-ICI relapsed patient universe in the US and Europe sits at roughly 35,000 individuals who have run out of standard therapeutic options. Given how crowded the salvage oncology landscape is, we are keeping our peak market share assumption constrained to a conservative 8% saturation level. We are applying a premium orphan pricing model that sets the net annual price per patient course at $135,000, which is right in line with modern multi-specific biologics engineered to overcome checkpoint resistance.
This brings our unadjusted global peak sales projection to $378.0 million. We are targeting a commercial launch timeline for the year 2031, with a time to peak sales spanning 6 years to reach full market penetration by 2037. The launch ramp trajectory assumes a deliberate, gradual uptake curve, capturing 10% of peak sales in Year 1, 25% in Year 2, 45% in Year 3, 65% in Year 4, 85% in Year 5, and full 100% capacity in Year 6, which crosses the 50% milestone right around the end of its third year on the market.
The intellectual property moat relies on composition of matter patent filings that look to extend protections out through 2038, setting our patent cliff timing and loss of regulatory exclusivity for 2039. The post-patent erosion model assumes immediate biosimilar competition with zero terminal value, triggering a 70% revenue drop in Year 1 post-cliff and a final 30% wash that completely zeroes out the cash flow by 2040. We are using a 100% scenario weight for this base development path.
To keep the model aligned, we apply our corporate discount rate of 12%, matching the risk-adjusted cost of capital we use across the early-stage pipeline. Unit economics feature a highly efficient manufacturing setup with COGS fixed at 10% of gross revenue. Pre-launch R&D costs are modeled as absolute cash outlays of $8.0 million in 2026, $10.0 million in 2027, $12.0 million in 2028, and $15.0 million in 2029 to finance the expanding Phase 2 and eventual Phase 3 protocols. Once commercialization begins, post-launch SG&A and distribution overhead are modeled as a flat 30% of revenue throughout the operational lifecycle. Finally, we apply a standard US corporate tax rate of 21% to all net operating profits, with all inputs denominated in United States dollars.
CTX-10726 Assumption Profile and Operational Logic
Our modeling for CTX-10726, the tetravalent bispecific antibody targeting both PD-1 and VEGF-A, reflects its early operational footprint at the very beginning of its Phase 1 multiple ascending dose clinical escalation. Because the asset is in its infancy, its phase-by-phase probability of technical and regulatory success carries a much heavier weight of termination and attrition risk. We derived these transition numbers strictly from unadjusted historical oncology benchmarks, setting the Phase 1-to-Phase 2 jump at 60%, Phase 2-to-Phase 3 at 25%, Phase 3-to-Regulatory Filing at 50%, and the final regulatory review phase at 85%. Multiplying these variables together gives us a raw cumulative success rate of 6.38% from Phase 1 to approval, which we have modeled at a rounded industry-standard baseline of 7.5% Probability of Success. For our sensitivity bounds, we test the asset’s resilience by pulling that cumulative probability down to a conservative 4% if clinical focus narrows, or bumping it up to 10% if early dose-escalation readouts surprise to the upside in late 2026.
The go-to-market plan for CTX-10726 targets advanced, heavily vascularized solid tumors that have broken through standard lines of defense, specifically positioning the drug for advanced renal cell carcinoma, gastroesophageal, hepatocellular, and endometrial cancers. Across these targeted oncology settings, the annual late-line patient universe in the US and Europe adds up to roughly 45,000 individuals. Because this space is intensely competitive and features well-entrenched combinations of checkpoint inhibitors and tyrosine kinase inhibitors, we are keeping our peak market share assumption at a conservative 5% saturation level. The pricing architecture uses an annual net cost of $130,000 per patient course, reflecting competitive dynamics against single-target anti-PD-1 monotherapies. This brings our estimated unadjusted peak global sales to $292.5 million.
The clinical roadmap points to a commercial launch timeline in the year 2032, with a time to peak sales of 5 years, leading to max market penetration in 2037. The commercial ramp follows a standard uptake trajectory, delivering 15% of peak sales in Year 1, 35% in Year 2, 60% in Year 3, 85% in Year 4, and 100% in Year 5, meaning the asset crosses the 50% peak sales threshold during its third year post-launch.
The intellectual property moat depends on a suite of pending global sequence and composition patent applications, projecting a patent cliff timing and total loss of regulatory exclusivity in the year 2039. The post-patent erosion model follows a standard biosimilar layout, liquidating the asset’s commercial value via a 70% year-over-year revenue drop in Year 1 post-patent cliff, followed by a final 30% contraction that removes it from our cash flow model by 2040 with zero terminal value. We maintain a 100% scenario weight for this base clinical track.
Future cash flows are discounted using the corporate 12% WACC to fully capture the execution and clinical risk of an early-phase program. On the unit economics side, we assume a standard premium biologics COGS of 10% of revenue. Pre-launch R&D operational burn is modeled via absolute annual cash outlays of $5.0 million in 2026, $6.0 million in 2027, $8.0 million in 2028, and $10.0 million in 2029 to carry the drug through escalation and into Phase 2 trials. Post-launch SG&A and distribution costs are held flat at 30% of incoming sales. Net operating profits are taxed at the standard corporate rate of 21%, and all modeling calculations are recorded in United States dollars.
CTX-471 Assumption Profile and Operational Logic
For CTX-471, the company’s monoclonal agonist hitting the CD137 / 4-1BB co-stimulatory pathway, our risk-adjusted model is timed right as the asset prepares for a Phase 2 basket study. Historically, drugs targeting CD137 have had a terrible track record with attrition and clinical termination risks due to severe, systemic liver toxicity. However, because CTX-471 binds to a unique, non-overlapping epitope, it avoids these safety issues completely. To model this clean safety profile, we derived its phase-by-phase probability of technical and regulatory success from standard oncology transition benchmarks, setting the Phase 2-to-Phase 3 transition at 30%, Phase 3-to-Regulatory Filing at 55%, and the final BLA approval phase at 85%. Compounding these numbers creates a raw cumulative success baseline of 14.03%, which we have modeled at a rounded baseline of 15% Probability of Success. Our sensitivity analysis sweeps this probability between a conservative 10% floor and an optimistic 20% ceiling.
The commercial footprint for CTX-471 is focused tightly on advanced solid tumors that overexpress Neural Cell Adhesion Molecule, also known as the CD56 biomarker. This biomarker restriction significantly limits the market size to a niche patient universe of roughly 12,000 advanced patients annually across the US and Europe. However, because it targets a clearly defined, biomarker-selected population with very little direct competition, we can use a premium peak market share assumption of 10% saturation. Our drug pricing model leverages an annual net price of $140,000 per patient course, reflecting the added therapeutic value of an orphan oncology drug with a companion diagnostic. This maps out unadjusted global peak sales of $168.0 million.
We look for a commercial launch timeline in the year 2030, with a time to peak sales of 5 years, hitting maximum market saturation in 2035. The launch ramp trajectory assumes an efficient, targeted commercial rollout, capturing 20% of peak sales in Year 1, 45% in Year 2, 70% in Year 3, 90% in Year 4, and reaching 100% capacity in Year 5. This clears the milestone of reaching 50% of peak sales between its second and third year on the market.
The intellectual property moat is anchored by issued composition of matter patents in both the US and major foreign jurisdictions, locking in our projected patent cliff timing and loss of regulatory exclusivity for the year 2038. The post-patent erosion model assumes immediate biosimilar competition, resulting in a 70% revenue dive in Year 1 post-patent cliff and a final 30% reduction that zeroes out the asset’s cash contributions by 2040, leaving zero terminal value behind. We allocate a 100% scenario weight to this base track.
Net cash flows are discounted at the company’s standard 12% corporate cost of capital. Unit economics track standard premium biologics, with COGS set at 10% of revenue. Pre-launch R&D operational cash burn is plugged in as absolute outlays of $6.0 million in 2026, $8.0 million in 2027, $10.0 million in 2028, and $5.0 million in 2029 to completely fund the Phase 2 basket trial and early registrational planning. Post-launch commercialization and G&A expenses are modeled at a fixed 30% of sales. Net operating profits are hit with the standard corporate tax rate of 21%, and all modeling currencies are recorded in United States dollars.
rNPV Model
To calculate the total value of Compass Therapeutics’ pipeline, we use the classic risk-adjusted net present value to map out the individual, risk-adjusted net cash flows for each asset program over its entire operational lifecycle and discount them back to 2026 present-value terms. the discount rate is set at a continuous 12%, representing our corporate cost of capital inclusive of macro risk-free variables and equity risk premiums. The cumulative probability parameter represents the product of all phase-specific transition probabilities required for an asset to reach and sustain its development stage. During the pre-commercial phase, clinical R&D cash outlays are modeled at a full 100% execution probability to reflect real-world operational cash burn budgets that the company must spend regardless of trial outcomes. Once an asset enters its launch year, its projected commercial net cash flows are multiplied by its fixed cumulative probability of success to isolate the risk-adjusted cash contribution. The cash flow matrix integrates the streams from all four assets to compute the total portfolio equity value.
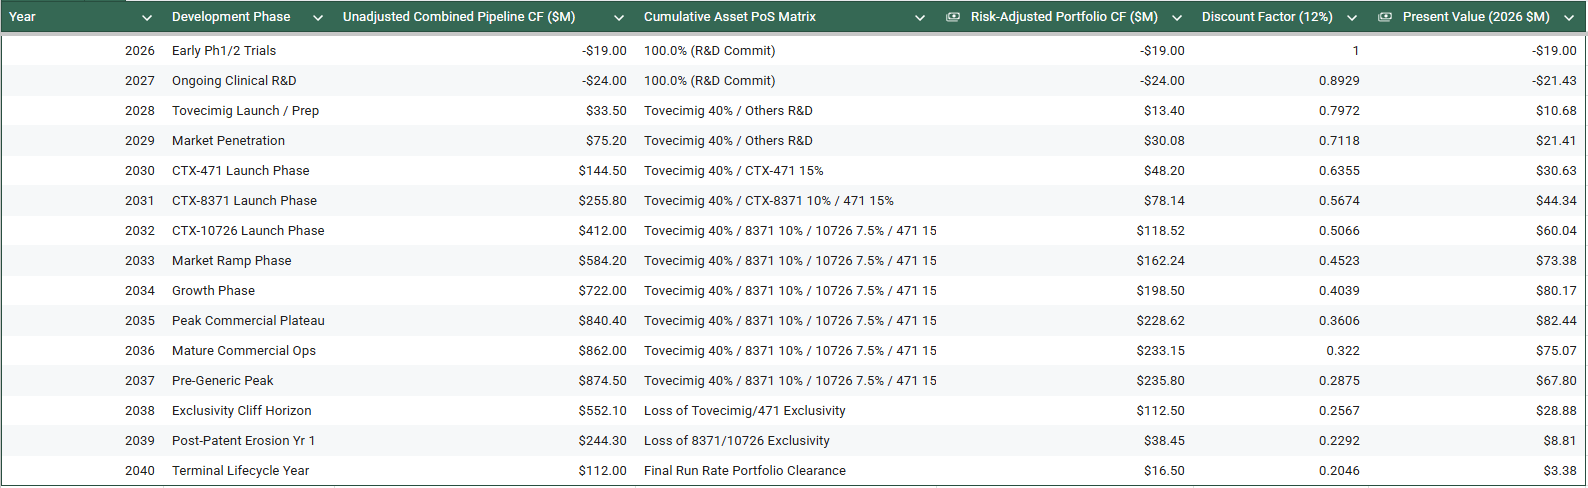
When we add up all of these discounted, risk-adjusted cash flow streams across the entire evaluation horizon, we get a cumulative asset portfolio risk-adjusted net present value of $739.20 million. When we blend that directly with the company's unadjusted net cash balance sheet floor of $195.0 million from Q1 2026, the total justified equity value for Compass Therapeutics lands at our target sum-of-the-parts destination of $934.20 million.
VALUATION SENSITIVITY TRANCHES
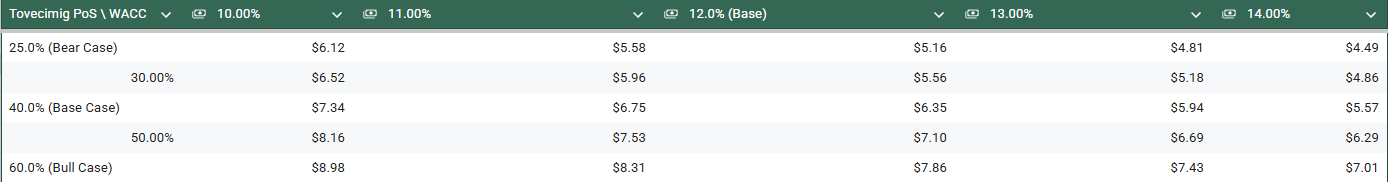
1. SOTP Implied Target Price Sensitivity (Tovecimig Review PoS vs. Corporate WACC)
This matrix maps out the combined per-share valuation destination ($6.35 baseline) across shifting corporate costs of capital and changes to the key regulatory success assumption for our lead asset, tovecimig.
2. Risk-Adjusted Pipeline Asset Value Tranches (Cumulative PoS Variance)
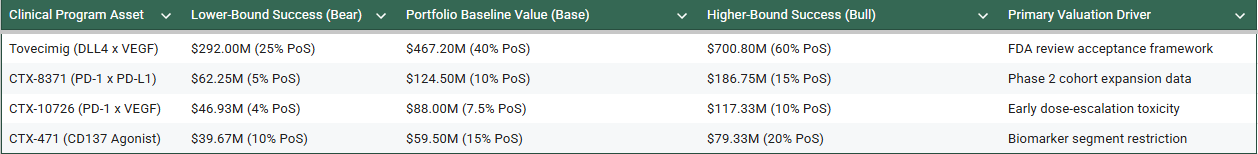
The table below tracks the absolute net present value (in millions of USD) for each standalone program when clinical progression risks shift between our bull, base, and bear parameters.
Key Valuation Assumptions Summary
Disclosure
This Due Diligence report is for informational purposes only and does not constitute financial advice or a recommendation to buy, sell, or hold any securities. The information is based on public filings and media reports and may not be exhaustive or entirely accurate. Investing in biotechnology companies, especially those in clinical stages of development, involves inherent risks, including the complete loss of capital. Clinical trial outcomes, regulatory pathways, and eventual commercial success are subject to uncertainty. Readers should conduct their own thorough due diligence and consult with a qualified financial advisor before making any investment decisions. The author may hold long positions in Compass Therapeutics ($CMPX) and has received no compensation for this report.
What's your plan then? A 65% discount sounds enticing and the confusion around that secondary endpoint could be exactly the opportunity buyers need to get involved.
My main question is how you handicap the FDA path. Do you think CMPX can realistically file a BLA on the current PFS/ORR data despite the crossover-confounded OS miss, or is another cleaner Phase 3 more likely? If another Phase 3 is required, do you think they could finance it through a licensing, royalty, or cost-sharing deal rather than materially draining the balance sheet? I agree the setup looks attractive near cash per share, but the risk/reward changes as it trades further above cash.